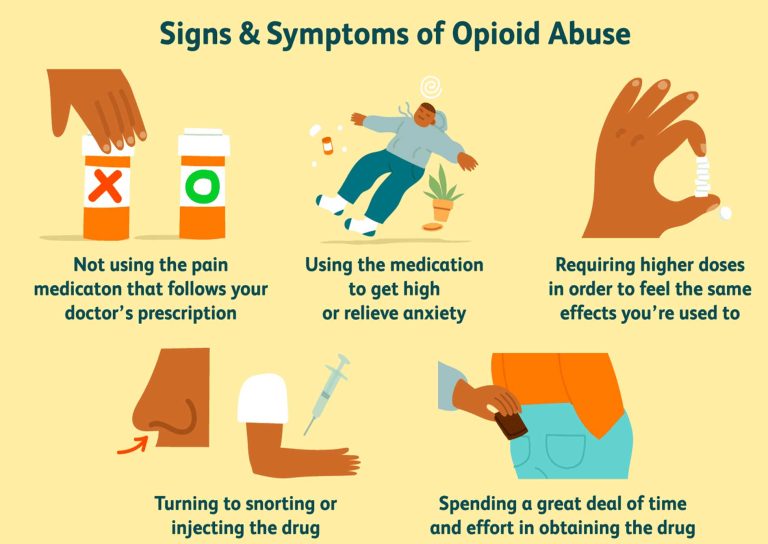
4 Common Heroin Withdrawal Symptoms
4 Common Heroin Withdrawal Symptoms
Heroin withdrawal brings four symptoms: agitation, muscle pain, sleep disruption, and physical illness. What to expect and how medical detox helps.
The body aches hit first, and they hit hard. That is the symptom people remember most when they tell you what heroin withdrawal actually felt like: a full-body cramp that will not let up, paired with shaking, sweating, and a stomach that will not stop churning. Heroin withdrawal brings four symptoms most people go through in some combination: agitation and anxiety, muscle pain and weakness, disrupted sleep, and physical illness.
Key points
- Heroin withdrawal typically begins 8 to 24 hours after the last dose and peaks in the first few days.
- The four most common symptoms are agitation, muscle pain, sleep disruption, and physical illness such as nausea, vomiting, and a runny nose.
- Intensity varies by dose, duration of use, and individual biology, but the pattern is consistent.
- A medically managed heroin detox uses medication to ease symptoms and monitors for complications like dehydration.
What is heroin withdrawal?
Heroin withdrawal is what happens when your body, which has adapted to the presence of the drug, suddenly has to function without it. Dependence means your nervous system has recalibrated itself around the drug’s effect, so removing it upsets that balance until it can reset. You feel the reset as pain, restlessness, and illness, building over hours and then easing.
This is a sign your body was physically dependent. The symptoms are the body’s predictable response to a missing drug, and they do not mean something is permanently wrong. They mean the system is working, in an uncomfortable way, to get back to baseline.
What do the four main symptoms look like?
Each of the four symptoms has a recognizable pattern. They often overlap, so you may experience two or three at once.
Agitation and anxiety is the one people notice first. It ranges from a low-grade restlessness to a deep, grinding irritability where nothing feels right and you cannot sit still. Some people describe it as a persistent sense of dread without a specific cause, and it does not respond to distraction the way normal anxiety does.
Muscle pain and weakness is the second, and for many it is the most physically punishing. It starts in the back and legs, then spreads, making it hard to get comfortable in bed or hold a normal posture. The aches can be so intense that simple movements like rolling over feel like effort.
Sleep disruption is the third, and it goes two directions. Some people cannot fall asleep at all, lying awake with their body screaming at them. Others fall into a deep, exhausted sleep but wake up feeling as though they lost time. Both patterns can stretch well past the first few days.
Physical illness is the fourth and, for many people, the reason they finally call for help. Nausea, vomiting, diarrhea, a runny nose, sneezing, and goosebumps that will not stop are all part of it. Dehydration from the vomiting and diarrhea is the main medical concern, which is why someone needs to be monitoring you.
Exhibit 1
The four symptoms arrive in overlapping waves, each with its own shape
Four panels showing agitation, muscle pain, sleep disruption, and physical illness, each with its characteristic pattern and what it feels like from the inside
Why do these symptoms hit so hard?
The intensity of withdrawal depends on how much your body had to adapt. Someone who used a heavy dose daily for months has a nervous system that is deeply adapted, and the shock of removing the drug is proportional to that adaptation. There is no way to predict exactly how hard it will hit for any one person, and that uncertainty is part of what makes the first days so frightening.
Your body is trying to restore a balance it lost while the drug was present, and the symptoms are the cost of that restoration.
What happens if you try to quit on your own?
Most people who attempt heroin withdrawal at home describe the first day or two as the hardest part of their entire recovery. The symptoms are uncomfortable enough that the urge to use again, just to stop the pain, becomes overwhelming. Relapse in the first few days is the most common outcome of an unmonitored quit, because the physical misery is that severe and no one is there to help you through it.
There is also a medical risk. Dehydration from vomiting and diarrhea can become serious, especially if you stop drinking water because everything you touch tastes wrong. In more severe cases, people report hallucinations, confusion, and memory problems, and in rare cases severe muscle spasms or seizures can occur. These are uncommon, but they are the kind of thing that is dangerous when no one is watching. A medically supervised detox closes that gap.
Exhibit 2
Home withdrawal and medically managed detox diverge at the point of monitoring
Two lanes showing an unmonitored home quit where dehydration and relapse risk go unchecked, and a supervised detox where a physician adjusts medication as symptoms shift
What does medically managed heroin detox look like?
In a heroin detox program at Pines, a physician assesses your history, your current physical state, and the severity of your dependence, then builds a medication plan around it. The most common approach is a taper: a carefully managed reduction of the opioid effect that eases the peak of the withdrawal while your body relearns how to function without the drug. Nursing staff monitor your symptoms around the clock, and nurses adjust your medication as things shift.
The medication is the tool, but the medical supervision is the point. Someone is watching your vitals, your hydration, your mental status, and adjusting the plan when something changes. That is the difference between white-knuckling through the hardest stretch and getting through it with a physician in the room.
After the acute phase, the team transitions you into residential inpatient treatment if you and the medical team decide that is the right next step. The same people who monitored your detox carry your history forward, so you are not starting over with clinicians who have to figure out what happened in the first few days. Aftercare planning begins during the residential stay. The plan covers the weeks after discharge, when the cravings are still loud.
Questions people ask
How long does heroin withdrawal last?
The acute phase usually peaks in the first few days and then tapers. Some symptoms, particularly insomnia and anxiety, can linger for a few weeks after the worst of it has passed. The exact timeline is different for everyone, but the general shape is a sharp rise, a peak, and a slow decline rather than an abrupt stop.
Can heroin withdrawal kill you?
Directly, it is rare. The main medical risk is dehydration from vomiting and diarrhea, which can become serious if you stop drinking. In very rare cases, severe muscle spasms or seizures can occur. This is why a medically supervised setting is the standard of care.
What medication is used in heroin detox?
The most common approach is a taper with a long-acting opioid such as methadone or buprenorphine, which reduces the severity of withdrawal while the body adjusts. The specific drug and schedule depend on your history, your current use, and your physical condition, and are set by the physician on your case. The goal is to get you through the acute phase with minimal suffering.
Is heroin detox the same as opioid detox?
Heroin detox is a specific case of opioid detox, but the two are not identical in practice. Heroin has a shorter half-life than many other opioids, which means withdrawal can come on faster and peak more sharply. The medication and monitoring protocol are tailored to that, and the physician builds the taper around the specific drug you have been using.
If the person in front of you is in the middle of a heroin withdrawal, the first thing that helps is getting them in front of a physician who can assess what is happening and what the next step should be. You do not need to figure it all out before you call. The admissions team at Pines Recovery Life answers around the clock, and a conversation takes a few minutes. Call (855) 981-8935.